Busan BGSS Eye Clinic · JCI-Accredited Ophthalmology Since 1997 · 7-Language Patient Care
JCI-Accredited · Since 1997
en-US

ICL (Lens Implantation) · Needs Clinic Confirmation
V Toric ICL
V-Toric ICL is a third-generation astigmatism-correcting lens implantation technique developed by the BGSS network — a proprietary surgical approach that corrects high myopia and astigmatism simultaneously through vertical toric lens
Schedule a ConsultationWhat Is V-Toric ICL? Vertical Toric Lens Implantation for Astigmatism in Busan
V-Toric ICL is a third-generation astigmatism-correcting lens implantation technique developed by the BGSS network — a proprietary surgical approach that corrects high myopia and astigmatism simultaneously through vertical toric lens insertion, solving the lens rotation problem that has long been the central limitation of conventional toric ICL surgery. Where standard toric ICL inserts the lens along the horizontal meridian and compensates for rotation risk by using an oversized lens that fits tightly inside the eye, V-Toric ICL inserts the lens along the vertical meridian — where natural ocular diameter is consistently greater — allowing a correctly sized lens to sit stably without the tight-fit mechanism that causes long-term intraocular pressure rise, endothelial cell damage, and cataract and glaucoma risk.
The core clinical principle behind V-Toric ICL is straightforward: correcting myopia alone without correcting astigmatism cannot produce maximum corrected vision. Even a toric lens that initially corrects astigmatism fails if it rotates post-implantation — a rotation of more than 10 degrees causes significant astigmatic axis displacement, equivalent to implanting a completely wrong-powered lens and causing vision deterioration at all distances. Approximately 70% of astigmatism-correcting ICL procedures in Korea currently use oversized lenses to prevent this rotation — an approach that manages the short-term problem while creating long-term structural risks inside the eye. V-Toric ICL eliminates both problems: rotation is prevented by vertical insertion and gravity-assisted fixation, not by lens oversizing.
Developed from 66,000+ ICL clinical cases and 24 years of lens implantation experience at the BGSS network, V-Toric ICL was introduced in 2017 and has since received Best Poster recognition at the 35th Asia-Pacific Cataract and Refractive Surgery Society, Best Paper Award at KSCRS, and academic validation at the 129th Korean Ophthalmological Society — establishing it as a clinically proven alternative to conventional horizontal toric ICL at the Seomyeon, Busanjin-gu clinic.
Who Is a Candidate for V-Toric ICL in Busan?
V-Toric ICL at Busan BGSS Eye Clinic in Seomyeon is designed for patients with myopia combined with significant astigmatism who need simultaneous correction of both conditions — particularly those for whom conventional toric ICL presents long-term safety concerns. Our team at the Busanjin-gu, Busan clinic conducts precise ocular space measurement and astigmatic axis evaluation before recommending V-Toric ICL.
Ideal candidates include:
Patients with high myopia and high astigmatism requiring simultaneous correction of both refractive components — leaving residual astigmatism after myopia correction alone produces blurred vision at all distances at the Seomyeon facility
Those concerned about long-term toric ICL safety — patients who have been advised that conventional toric ICL requires an oversized lens and are concerned about the associated IOP and endothelial cell risks at the Busan clinic
Patients with larger pupils or night vision concerns — V-Toric ICL's correctly sized lens and stable axis positioning support better optical quality and reduced night halos compared with rotation-prone conventional toric designs
Those who have experienced toric ICL rotation or axis displacement following surgery at another clinic and are seeking a more stable re-correction approach at the Seomyeon, Busanjin-gu facility
Patients unsuitable for laser astigmatism correction due to thin corneas, high prescription, or corneal irregularity — V-Toric ICL corrects both myopia and astigmatism without touching the cornea at the Busanjin-gu, Busan clinic
International patients traveling to Busan for astigmatism-correcting lens implantation who require a clinically validated, award-winning technique with multilingual coordination
Patients with insufficient anterior chamber depth, active ocular disease, or unstable prescriptions are not suitable for V-Toric ICL. Our team evaluates all eligibility criteria at the pre-operative assessment and recommends alternative pathways where needed.
Our Team at Busan BGSS Eye Clinic, Seomyeon
V-Toric ICL at Busan BGSS Eye Clinic is performed and managed by our team of five senior directors, each holding concurrent academic appointments at major regional universities in Busan. The V-Toric ICL technique requires precise mastery of vertical ocular space measurement, astigmatic axis identification, lens sizing calculation, and insertion angle control — a combination of skills developed through 24 years of ICL practice and 66,000+ lens implantation cases at the BGSS network.
The BGSS network's proprietary astigmatism correction algorithm — the foundation of V-Toric ICL — was developed by the network's founding director, who was selected as an ICL educator in 2006 and appointed inaugural chairman of the ICL Key Opinion Leader Forum in 2024. The Busan BGSS team at the Seomyeon, Busanjin-gu clinic applies this algorithm and surgical approach directly, supported by the network's designation as the Asia-Pacific Regional Center for EVO ICL Training in 2026. Our team's V-Toric ICL results have been presented and recognized at the three most significant refractive surgery academic forums in the Asia-Pacific region.
The V-Toric ICL Advantage: Why Vertical Insertion Changes Everything
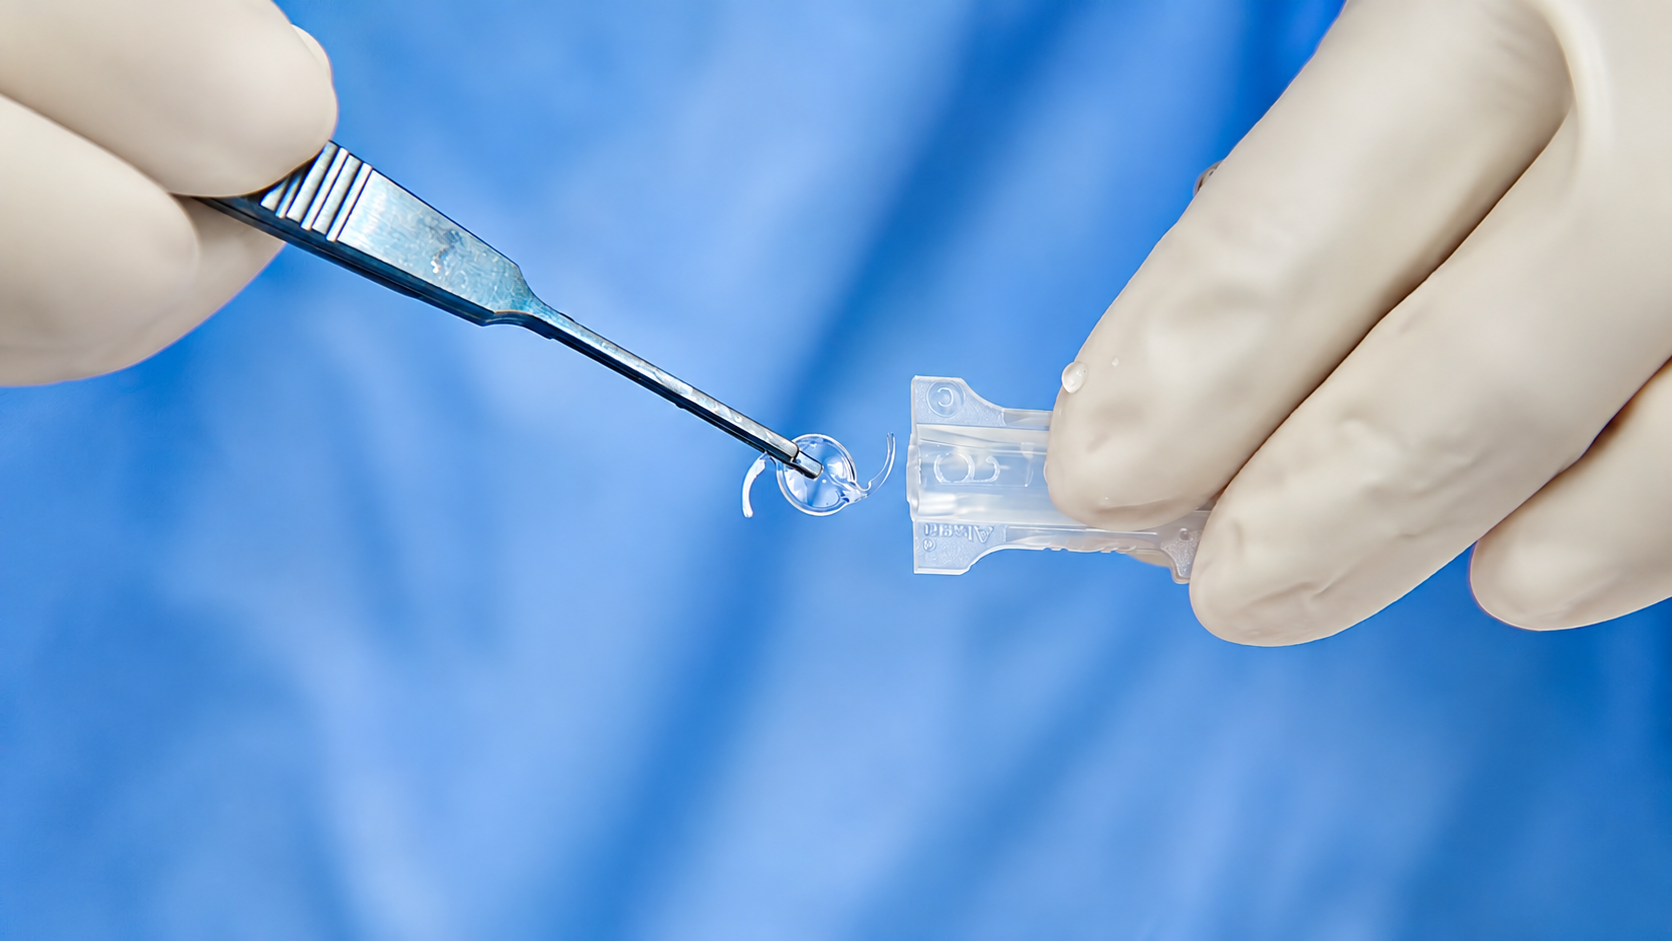
Conventional toric ICL inserts the lens horizontally, along the shorter ocular meridian. To prevent rotation in this position, clinics use a lens larger than the eye's horizontal diameter — creating a tight fit that stops rotation by force. This works initially, but over 10 or more years the sustained pressure from an oversized lens raises intraocular pressure, damages corneal endothelial cells, and risks cataract and glaucoma development.
V-Toric ICL at Busan BGSS Eye Clinic in Seomyeon, Busanjin-gu solves this through three design principles:
1\. Precise Ocular Space Measurement: The vertical ocular diameter is consistently greater than the horizontal (for example, 11.22mm vertical vs 11.01mm horizontal). By inserting the toric lens along the vertical meridian, our team at the Seomyeon clinic places the lens in a wider space — allowing a correctly sized lens to fit with room to spare, eliminating peripheral lens contact and the side effects that stem from it.
2\. Astigmatic Axis Stabilization Through Gravity: Vertical insertion uses the natural downward gravitational force on the lens as a fixation mechanism — not tight sizing. This gravity-assisted stabilization keeps the lens axis change within 3 degrees, compared with up to 90-degree rotation possible with horizontal insertion. Rotation beyond 10 degrees causes clinically significant axis displacement; V-Toric ICL at the Busanjin-gu, Busan facility keeps rotation well within the safe threshold even at low vaulting levels.
3\. Optimally Sized Lens — No Oversizing Required: Because the vertical meridian provides sufficient space, V-Toric ICL uses a correctly sized lens rather than a deliberately oversized one. This eliminates the high-vaulting mechanism responsible for IOP rise, endothelial cell damage, and long-term cataract and glaucoma risk. Clinical data shows V-Toric ICL achieves low rotation risk even at low vaulting — a combination not achievable with conventional horizontal toric ICL.
V-Toric ICL Procedure Steps and Recovery Timeline
V-Toric ICL at Busan BGSS Eye Clinic in Seomyeon, Busanjin-gu is performed under topical anaesthetic drops. The full pathway:
Pre-Operative Ocular Space and Axis Assessment — Our team measures precise vertical and horizontal ocular diameters, anterior chamber depth, corneal topography, astigmatic axis, and endothelial cell count at the Seomyeon clinic. These measurements determine lens size, power, insertion angle, and axis alignment — all six parameters of the V-Toric ICL surgical design: lens power, lens size, astigmatism power, astigmatic axis, insertion position, and insertion angle.
Astigmatic Axis Marking and Alignment — Before lens insertion, the astigmatic axis is precisely marked and confirmed at the Busanjin-gu, Busan facility. Accurate axis identification at this stage is essential — any deviation propagates through the entire correction, making pre-operative marking the most critical preparatory step in toric ICL surgery.
Vertical Toric ICL Insertion — The V-Toric ICL is inserted through a small self-sealing incision and positioned along the vertical meridian at the Seomyeon, Busanjin-gu clinic. No corneal ablation occurs at any stage. The lens is aligned precisely to the pre-marked astigmatic axis and positioned to use gravity as its primary stabilization mechanism.
Lens Position and Axis Confirmation — Following insertion, our team at the Busan BGSS facility confirms lens centration, vaulting level, axis alignment, and intraocular pressure before the patient is discharged with prescribed anti-inflammatory and antibiotic drops and detailed aftercare instructions.
Next-Day Follow-Up — A review at the Seomyeon, Busanjin-gu clinic the day after surgery assesses uncorrected visual acuity, lens position, axis stability, and IOP. BGSS clinical data shows 97% of V-Toric ICL patients achieve 0.9 or better uncorrected vision at this first review.
3-Month Monitoring Protocol — Our team at the Busanjin-gu, Busan clinic monitors lens axis stability, visual acuity, IOP, and endothelial cell count at one-month and three-month intervals. BGSS 3-month follow-up data across 230 eyes shows average vision of 1.0 at one month and 0.9–1.0 at three months, with 99% stable lens fixation and only approximately 1% requiring lens position adjustment.
V-Toric ICL Results, Safety, and Longevity
BGSS network clinical data from 230 eyes over a 3-month follow-up period demonstrates: 97% achieve 0.9 or better uncorrected vision the next day; average vision of 1.0 at one month; average vision of 0.9–1.0 at three months; 99% stable lens fixation; and only approximately 1% requiring lens position adjustment — with average vision maintained at 0.9 even in adjusted cases. Astigmatic axis change in V-Toric ICL is confirmed within 3 degrees, compared with up to 90-degree rotation possible in conventional horizontal toric ICL. Results vary by individual and no specific outcome is guaranteed.
The safety profile of V-Toric ICL at the Seomyeon clinic is structurally superior to conventional toric ICL in two critical respects: correctly sized lens eliminates high-vaulting IOP risk and endothelial cell damage, and gravity-assisted vertical fixation eliminates the need for the tight-fit oversizing that causes long-term cataract and glaucoma risk. These advantages have been academically validated at three major refractive surgery conferences in 2023. Potential side effects include temporary light sensitivity, mild halos, and transient IOP variation — generally resolving as healing progresses. Serious complications are uncommon and our team's pre-operative protocol minimizes risk further.
V-Toric ICL produces stable, long-term simultaneous correction of both myopia and astigmatism. The correctly sized, gravity-stabilized lens maintains axis position over time — eliminating the progressive axis drift that causes vision deterioration in rotation-prone conventional toric ICL. Age-related changes such as presbyopia develop independently and are not addressed by the procedure.
Why Choose Busan BGSS Eye Clinic in Seomyeon for V-Toric ICL?

V-Toric ICL is not a generic procedure — it is a proprietary BGSS surgical technique developed through 24 years of ICL practice, 66,000+ lens implantation cases, and a network-wide commitment to solving the rotation problem that affects conventional toric ICL. Busan BGSS Eye Clinic in Seomyeon, Busanjin-gu applies this technique directly, with our team of five senior directors holding university appointments across Busan's leading medical institutions bringing the anterior segment expertise, ICL experience, and astigmatism algorithm mastery that V-Toric ICL demands. As the founding BGSS location since 1997 with 330,000+ vision correction surgeries, the Seomyeon clinic's credentials are clear:
First ophthalmology clinic in Korea to receive JCI accreditation — four cycles
Asia-Pacific Regional Center for EVO ICL Training (2026) and Advanced Regenerative Medicine Institution (2026)
Best Poster Award — 35th Asia-Pacific Cataract and Refractive Surgery Society (2023)
Best Paper Award — KSCRS Korean Cataract and Refractive Surgery Society (2023)
Academic validation — 129th Korean Ophthalmological Society (2023): vertical insertion proven superior to horizontal as new standard
Key Medical Tourism Cooperative Institution, City of Busan — multilingual support in Chinese, English, Japanese, Mongolian, Russian, Vietnamese, and Indonesian
Patient Experiences: V-Toric ICL at Busan BGSS Eye Clinic, Seomyeon
Patient Vignette 1 — High Myopia with High Astigmatism, Late 20s
A patient in their late 20s traveling to Busan had been told at another clinic that their high astigmatism would require an oversized toric lens with associated long-term IOP concerns. Following pre-operative ocular space measurement at the Seomyeon, Busanjin-gu clinic, our team confirmed vertical diameter suitability for V-Toric ICL. Both myopia and astigmatism were corrected simultaneously in a single procedure, and the patient achieved 0.9 or better uncorrected vision at the next-day review with stable axis alignment confirmed. Results vary; no outcome is guaranteed.
Patient Vignette 2 — Toric ICL Rotation Concern, Early 30s
A patient in their early 30s at the Busanjin-gu, Busan clinic had researched conventional toric ICL and was concerned about lens rotation and long-term IOP effects. Following assessment confirming sufficient vertical ocular diameter at the Seomyeon facility, V-Toric ICL was performed using the gravity-assisted vertical insertion approach. At the three-month follow-up, lens axis was confirmed within the stable threshold and average vision was maintained at 1.0. Individual results vary and no specific outcome is guaranteed.
Correct Myopia and Astigmatism Together — Book Your V-Toric ICL Consultation in Busan
If you have high myopia combined with significant astigmatism and want a single procedure that corrects both stably and safely — without oversized lenses, without rotation risk, and without the long-term IOP and endothelial concerns of conventional toric ICL — our team at Busan BGSS Eye Clinic in Seomyeon, Busanjin-gu is ready to evaluate your suitability for V-Toric ICL. With 66,000+ ICL cases, 24 years of lens implantation experience, three 2023 international academic recognitions, JCI accreditation, and Asia-Pacific EVO ICL Training Center status, the Seomyeon clinic offers the astigmatism correction expertise and ICL surgical depth that complex toric cases demand. International patients are fully supported in Chinese, English, Japanese, Mongolian, Russian, Vietnamese, and Indonesian.
**[Book Your Free V-Toric ICL Consultation at Busan BGSS Eye Clinic](/contact-us)
Other Services
Explore our comprehensive range of healthcare offerings tailored to your needs.

Dry Eye Diagnostic Testing
It is a spectrum of disorders with distinct underlying mechanisms — each requiring a different clinical response.
Learn More

Aqua IPL / Aqua Lifting
Dry eye syndrome is one of the most common and undertreated conditions in ophthalmology — affecting contact lens wearers, digital screen users, post-surgical patients, and adults over 40 with progressively declining tear film quality.
Learn More
Autologous Serum Eye Drops
Autologous serum eye drops are a specialized therapeutic preparation in which a patient's own blood is processed to extract the serum — which is then formulated as personalized eye drops.
Learn More